
 English


Learn how to evaluate bone reduction forceps by jaw geometry, box-lock alignment, material documentation, reprocessing needs and total-cost considerations before issuing an RFQ.
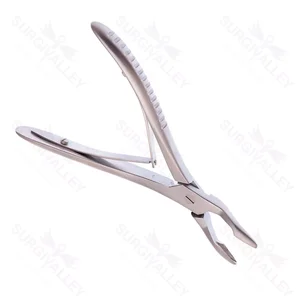
Selecting bone reduction forceps requires more than matching a catalogue name to a procedure or set list. Clinical and procurement teams must connect the intended handling requirement with jaw geometry, serration design, articulation, working length, material documentation and inspection criteria. A disciplined comparison helps teams distinguish a suitable bone holding forceps pattern from a superficially similar clamp.
The strongest sourcing process turns these requirements into observable acceptance points. Buyers should be able to review a sample, confirm that the jaws meet without scissor crossover, assess the box-lock and ratchet, and request clear evidence for the stated alloy and reprocessing guidance. The objective is not to prescribe a clinical technique, but to make the instrument specification precise enough for safe evaluation and consistent replacement.
Mechanical Precision: Box-Lock Alignment and Jaw Crossover Risks
The box-lock is central to the forceps’ closing action, jaw tracking and serviceability. During sample review, close the instrument gradually and observe whether the jaws meet evenly across their working length. The required acceptance point should be zero jaw scissor crossover: one jaw should not pass laterally across the other as the handles close. Also check for lateral play, uneven contact, rough movement, incomplete closure and a ratchet that releases or engages inconsistently.
These checks should be documented rather than treated as an informal visual impression. Record the instrument reference, nominal length, jaw configuration, handle style and any agreed tolerance or rejection criterion. A supplier sample that closes well once is not, by itself, evidence of production consistency, so the RFQ should request the inspection method and the way critical dimensions are controlled.
- Confirm jaw alignment through the full closing motion.
- Reject visible scissor crossover, binding or uneven jaw contact.
- Check box-lock movement for excessive play or roughness.
- Document the reference, dimensions and acceptance criteria.
- Separate clinical preference from measurable procurement requirements.
| Inspection point | What to observe | RFQ evidence |
|---|---|---|
| Jaw meeting | Even contact without crossover | Sample inspection record |
| Box-lock | Smooth articulation without obvious looseness | Functional inspection method |
| Ratchet | Consistent engagement and release | Mechanism acceptance criteria |
| Handles | Comfortable, symmetrical closure | Configuration drawing or sample approval |
Metallurgy Matters: Selecting Steel for Reprocessing Durability
Material selection should be supported by documentation rather than a broad label such as surgical stainless steel. ASTM F899 specifies requirements for wrought stainless steels used in surgical instruments, including chemical composition and mechanical properties relevant to corrosion resistance. [1] For a procurement review, ask the supplier to identify the proposed material designation and provide the applicable material documentation, while avoiding assumptions that a named alloy alone guarantees long service life.
Autoclave longevity also depends on the complete reprocessing environment. Cleaning chemistry, water quality, drying, loading, instrument condition and local validated procedures can all affect corrosion risk. Pitting should therefore be investigated as a system issue rather than attributed automatically to the steel. The RFQ can require care instructions, compatibility information and a defined process for reviewing corrosion, discoloration or surface damage.
Do not insert a sterilization temperature, exposure time or passivation treatment into the specification unless the facility has validated that requirement for the instrument and process. Instead, require the supplier’s documented reprocessing information and have the responsible clinical engineering or sterile processing team assess it against local procedures.
- Request the exact material designation and supporting documentation.
- Treat ASTM F899 alignment as a documented requirement, not a marketing phrase.
- Review cleaning, drying and steam-processing compatibility together.
- Ask how corrosion or surface damage should be assessed and reported.
- Avoid using an alloy name as a substitute for process validation.
Jaw Design: Atraumatic Serrations and Force Distribution
Atraumatic serrations are not simply a visual alternative to traditional teeth. Their spacing, depth, orientation and relationship to the jaw profile influence how the working end contacts the intended material. Buyers should define whether the requirement is a fine serrated surface, a more pronounced tooth pattern or another documented configuration, and should avoid treating these terms as interchangeable. The appropriate choice depends on the intended clinical application and the responsible user’s preference.
When reviewing a sample, inspect the transition from the serrated or toothed area to the jaw tip, the symmetry of both halves and the finish at the edges. Look for damaged peaks, blocked grooves, mismatched profiles or a surface that does not close uniformly. These observations can be converted into a receiving checklist without making unsupported claims about bite pressure or clinical outcomes.
Specify jaw geometry in terms that another supplier can reproduce: working-end profile, length, width, curvature, serration or tooth pattern, handle configuration and overall instrument length. Include a drawing or approved reference sample where the pattern is difficult to describe in words.
- Name the required serration or tooth pattern explicitly.
- Define working-end dimensions and curvature where relevant.
- Compare both jaw halves for symmetry and matching profile.
- Inspect grooves, edges and tips for manufacturing damage.
- Use an approved drawing or sample for ambiguous patterns.
Reprocessing Economics: Comparing Total Cost of Ownership
A purchase-price comparison does not show the full economic effect of reusable bone forceps. A practical total-cost review should include acquisition, inspection, cleaning and sterilization workload, tray or container capacity, inventory levels, repair or replacement activity, training and the cost of removing instruments from service. If a single-use alternative is being considered, add purchasing frequency, disposal, storage and supply continuity to the same framework rather than comparing unit prices alone.
Use facility data wherever possible. The relevant assumptions may include how many instruments are needed per set, how often a pattern is used, the time required for inspection, the observed replacement rate and the effect of a damaged instrument on tray completion. These figures should be treated as local planning inputs, not universal performance claims. A reusable program may appear economical under one workflow and less attractive under another.
The RFQ should ask suppliers to identify what is included in the quoted item, how replacements are matched to the original configuration and what documentation supports reprocessing. Procurement can then compare like for like across suppliers and preserve the information needed for future replenishment.
- Include acquisition and processing costs in the comparison.
- Account for inventory, tray capacity and replacement activity.
- Use local workload and usage data rather than generic assumptions.
- Compare reusable and single-use options using the same cost categories.
- Record configuration and documentation requirements for replenishment.
| Cost category | Reusable program | Single-use program |
|---|---|---|
| Acquisition | Initial instrument and replacement purchases | Recurring item purchases |
| Processing | Cleaning, inspection and sterilization workload | Usually reduced processing workload, subject to local policy |
| Inventory | Sets, spares and repair stock | Storage and supply continuity stock |
| End of service | Repair, replacement and disposal decisions | Disposal and waste-management costs |
Procurement Checklist: Specifying and Inspecting an RFQ
A clear RFQ should describe the instrument as a controlled configuration rather than relying on the phrase bone reduction forceps alone. State the intended instrument family, jaw pattern, serration or tooth requirement, working length, jaw dimensions, handle and ratchet configuration, material documentation, surface finish, reprocessing information, packaging expectations and required inspection records. If the instrument is intended to match an existing set, provide the current reference, photographs or drawing and the dimensions that must remain unchanged.
Before approval, inspect representative samples using the same checklist that will be used for receiving. Verify the identity and configuration, then assess jaw symmetry, box-lock alignment, closure, ratchet function, surface condition and documentation. Record deviations and resolve them before volume ordering. A supplier’s ability to provide a drawing, sample and change-notification process can be as important as a favourable unit quotation.
After deployment, trend recurring findings such as pitting, stiff joints, jaw mismatch, ratchet damage or unexplained configuration substitutions. This creates a feedback loop between sterile processing, clinical users and procurement. It also helps determine whether the original specification was incomplete or whether a supplier-control issue needs attention.
- Identify the pattern without relying on a generic name.
- Specify jaw geometry, dimensions, mechanism and material evidence.
- Require an approved sample or drawing before volume purchase.
- Use one inspection checklist for samples and receiving.
- Document deviations and review recurring service findings.
A More Defensible Forceps Sourcing Decision
Bone reduction forceps should be evaluated as a combination of working-end design, mechanical precision, material documentation and reprocessing economics. The practical minimum is a configuration that can be identified clearly, closes without jaw scissor crossover, has a controlled box-lock and is supported by appropriate material and care documentation. Those requirements give clinical and procurement teams a shared basis for sample approval and replacement decisions.
The next step is to convert the checklist into the facility’s RFQ and receiving workflow. Include the dimensions, jaw pattern, inspection points, documentation requirements and local cost assumptions, then obtain representative samples for multidisciplinary review before committing to a larger order.
Selected ENT and Maxillofacial products



Frequently asked questions
How do I verify box-lock alignment in bone reduction forceps?
Close the forceps slowly and observe the jaws from several angles through the full range of motion. They should meet in the intended relationship without one jaw crossing laterally over the other. Also check for binding, excessive play, uneven contact and inconsistent ratchet engagement. Record the result against the approved sample or drawing instead of relying on a general visual approval.
Does ASTM F899 alone prove that forceps will last through autoclave processing?
No. ASTM F899 can support a documented material requirement, but service life also depends on the selected material, manufacturing quality, cleaning chemistry, water quality, drying, handling and the facility’s validated reprocessing process. Ask for the exact material designation and supporting documentation, then evaluate the supplier’s care information against local sterile processing requirements.
How should an RFQ describe atraumatic serrations?
Describe the working-end pattern rather than using atraumatic as an undefined adjective. State whether the required surface is serrated or toothed, and provide the relevant dimensions, spacing, depth, orientation, jaw profile and approved reference where available. A sample or drawing is especially useful when the pattern must match an existing orthopedic instrument set.
What should be included in a reusable versus single-use cost comparison?
Use the same decision categories for both options: purchase, inventory, storage, processing workload, inspection, replacement, repair, waste and supply continuity. Add local usage and tray data where available. Avoid assuming that one format is always cheaper; the result depends on workflow, volume, staffing, replacement patterns and the facility’s procurement requirements.
Related reading
- 420 vs 440A Stainless Steel for Orthopedic Instruments
- Autoclave and Passivation Protocols for Surgical Scissors
- Reusable vs Single-Use Surgical Instruments: A Total-Cost Decision Framework
- How to Specify Surgical Instrument Dimensions, Working Ends, Handles and Configurations
Orthopedic Instrument Procurement & Forceps Specifications
Hospital procurement officers, clinical teams, and surgical leads can review engineering drawings, material test reports (ASTM F899 / ISO 13485:2016), and institutional quotation terms across the official Orthopedic Surgical Instruments Range catalog.
References
- ASTM F899 standard specifies requirements for wrought stainless steels used in surgical instruments, including chemical composition and mechanical properties critical for corrosion resistance. View source at www.vendorportal.ecms.va.gov
Related Posts

Oct 28, 2026 by Dr. Rachel Moore